Download and print our referral form, fill it out, and email or fax it to our office with your radiographs. We’ll take it from there.
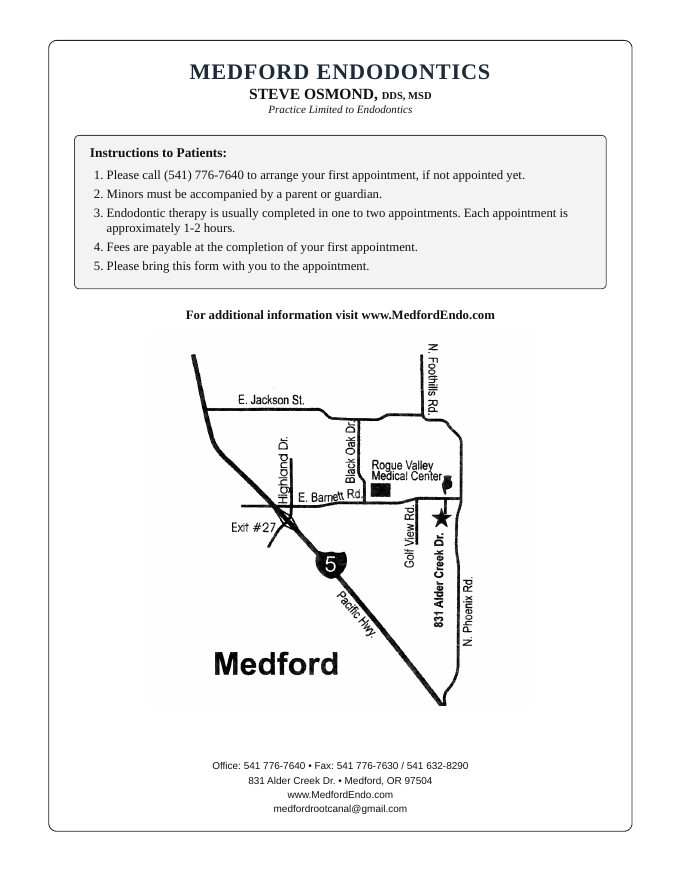
Download and print our referral form. The front is the referral; the back has instructions and a map for your patient.
Download PDF FormFill in the patient and referring dentist, circle the teeth that may need treatment, and check the treatment requested.
Email the completed form and radiographs to medfordrootcanal@gmail.com. You can also fax the form to (541) 776-7630 or (541) 632-8290. We’ll contact the patient or confirm with your office.
Email the OfficeA two-sided form: the front for your referral details, the back with instructions and directions for your patient.

Print double-sided if possible. Email the completed form to medfordrootcanal@gmail.com or fax it to (541) 776-7630 or (541) 632-8290.